
Double-target Vim+PSA deep brain stimulation
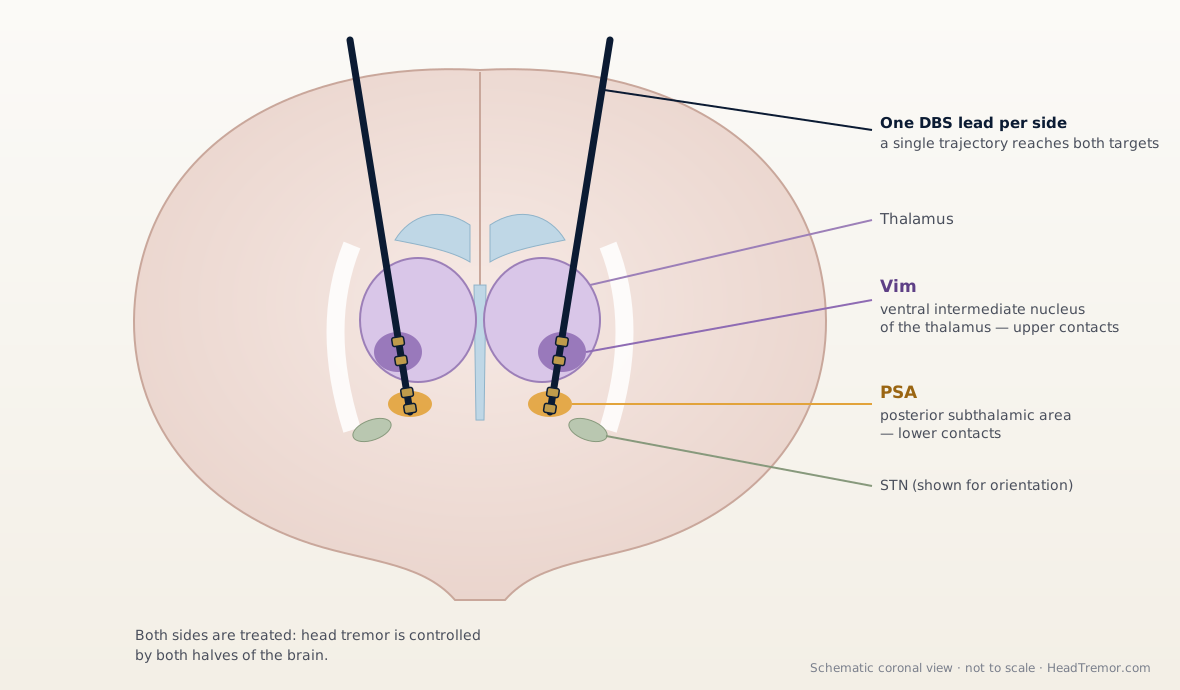
Double-target DBS stimulates two parts of the tremor circuit — the ventral intermediate nucleus of the thalamus (Vim) and the posterior subthalamic area (PSA) — along one electrode trajectory. Prof. Atilla YILMAZ, MD and colleagues reported it in 22 patients with rare tremor syndromes treated between 2019 and 2023, published in Stereotactic and Functional Neurosurgery in 2024. The mean tremor reduction was 89% (range 50–100%), and 6 of 7 patients with isolated head tremor reached a tremor score of 0. To the authors’ knowledge, it is the largest published series of double-target Vim+PSA DBS in rare tremor syndromes [1].
Key facts
- One trajectory reaches two tremor targets: the Vim and the PSA.
- Published series of 22 patients: mean tremor reduction 89% (range 50–100%) [1].
- 6 of 7 isolated head tremor patients reached a tremor score of 0 [1].
- Best contacts: Vim alone in 11%, PSA alone in 49%, both in 40% of patients [1].
- The target can be changed or added later by reprogramming, without surgery.
Why two targets
The Vim is the standard tremor target, but some tremors — head tremor, dystonic tremor, Holmes tremor — respond less reliably to Vim stimulation alone, and published reports describe the benefit of Vim-only DBS fading over time in some of these patients [1]. The PSA lies just below the Vim and contains the cerebellar fibers that carry the tremor signal in a compact bundle; open studies and randomized trials have suggested it can be more efficient than the Vim [1]. Because the two structures are close together, one carefully angled trajectory can reach both. The study’s authors concluded that the two are best seen as a continuum rather than separate targets [1].
How the trajectory is planned
The PSA is identified directly on MRI, relative to the red nucleus and the subthalamic nucleus; the Vim is calculated from standard anatomical landmarks. The electrode path is then tilted so that its deepest contact sits in the PSA while the third and fourth contacts reach the Vim, avoiding blood vessels and the ventricles. During surgery, test stimulation of both targets confirms the position [1].
The advantages
- Lower intensity at each site. Instead of driving one target hard, the stimulation can be shared between the Vim and the PSA. In our experience this makes numbness, speech and balance side effects easier to avoid; in the published series, settings were generally lower at both sites when both were used [1].
- A reserve for the future. If the disease progresses, or one target becomes less effective with time, the second target can be added.
- Switching without surgery. Moving the stimulation from the Vim to the PSA, or the other way round, is done by reprogramming the stimulator — the electrodes stay where they are.
- Little extra burden. Both targets lie along one trajectory, so no additional electrode is needed [1].
Published evidence from our center
Yilmaz A, Eray HA, Cakir M, Ceylan M, Blomstedt P. Deep Brain Stimulation with Double Targeting of the VIM and PSA for the Treatment of Rare Tremor Syndromes. Stereotactic and Functional Neurosurgery 2024;102:224–239.
- 22 patients treated between 2019 and 2023 with bilateral Vim+PSA DBS: 7 isolated head tremor, 4 dystonic tremor, 8 Holmes tremor, 2 voice tremor and 1 tremor caused by liver disease.
- Mean tremor score fell from 3.70 to 0.45 at 12 months; mean tremor reduction 89% (range 50–100%).
- 6 of 7 patients with isolated head tremor reached a tremor score of 0.
- Ratings were made blindly, with stimulation on and off, by two movement disorder specialists.
- To the authors’ knowledge, the largest published case series of double-target Vim+PSA DBS in rare tremor syndromes [1].
Read the article on PubMed (PMID 38934181) · How the double-target technique works
Results by tremor type (published series)
| Tremor type | Patients | Result at 12 months |
|---|---|---|
| Isolated head tremor | 7 | 6 of 7 reached a tremor score of 0; the seventh improved from 4 to 1 |
| Dystonic tremor | 4 | Tremor abolished in 3, reduced from 4 to 1 in 1; dystonia score improved 72% |
| Holmes tremor | 8 | 80% mean reduction (3.87 → 0.75) |
| Voice tremor | 2 | Vocal cord tremor improved to mild (too few patients for statistics) |
| Tremor due to liver disease | 1 | 75% improvement |
Source: Yilmaz et al., Stereotact Funct Neurosurg 2024 [1].
Where the best stimulation points were
After surgery, every contact was tested. In 11% of patients the best result came from the Vim alone, in 49% from the PSA alone, and in 40% from contacts in both. Most effective contacts clustered in the lower Vim and upper PSA. With both targets in use, lower settings were generally needed at each site [1].
Long-term results
Our longest-followed head tremor patient still has a tremor score of 0 six and a half years after double-target DBS; the score was 4 before surgery (our case series; results vary). If the effect lessens or the disease progresses, the second target can be activated by reprogramming, without new surgery.
 Play video: 40 Years of Head Tremor, 3 Years After DBS: Lasting Relief
Open the head tremor video library on this site.
Risks reported in the study
The article reports electrode repositioning in one patient, infections requiring removal and later re-implantation of an electrode in two patients, temporary slurred speech, and stimulation-induced unsteadiness that resolved by itself or after the settings were adjusted [1]. Reporting these openly is part of informed consent.
Who may benefit
- Isolated head tremor
- Dystonic head tremor where tremor is the main problem
- Holmes tremor and other secondary tremors
- Complex tremors involving the head, voice and limbs
- Essential tremor with prominent head tremor
Frequently asked questions
Is double-target DBS a second operation?
Is the double-target technique experimental?
Can the target be changed later without surgery?
Sources
- Yilmaz A, Eray HA, Cakir M, Ceylan M, Blomstedt P. Deep Brain Stimulation with Double Targeting of the VIM and PSA for the Treatment of Rare Tremor Syndromes. Stereotact Funct Neurosurg 2024;102:224–239. DOI 10.1159/000539162. pubmed.ncbi.nlm.nih.gov/38934181/
