
Deep brain stimulation for head tremor
Yes — deep brain stimulation (DBS) can stop or greatly reduce head tremor in carefully selected patients. Head tremor is harder to treat than hand tremor, and results depend on the cause, the brain target and the precision of the operation. Published studies show improvement in head tremor after thalamic DBS in essential tremor [1],[2] and after thalamic or subthalamic DBS in dystonic head tremor [3],[4]. In Prof. YILMAZ’s peer-reviewed series of 22 patients with rare tremor syndromes treated with double-target Vim+PSA DBS, the mean tremor reduction was 89% (range 50–100%), and 6 of 7 patients with isolated head tremor had a tremor score of 0 at 12 months, as rated blindly by two movement disorder specialists [5]. In our own case series of patients treated with DBS for head tremor, average improvement was 87%, and more than 70% of patients reached near-complete resolution (our case series; results vary).
Key facts
- DBS can stop or greatly reduce head tremor in carefully selected patients.
- Both sides of the brain are treated, because both control the neck [6].
- Double-target Vim+PSA: mean tremor reduction 89%; 6 of 7 isolated head tremor patients reached a score of 0 [5].
- The stimulator is switched on the day after surgery; the tremor usually stops at once after a successful operation.
- Longest follow-up: 6.5 years with a tremor score still at 0 (our case series).
- Cost: typically USD 30,000–45,000, all-inclusive, depending on package and device.
How DBS works
DBS delivers small, continuous electrical pulses to the part of the brain that generates the tremor rhythm. The system has three parts: thin electrodes in the brain, an extension wire under the skin, and a stimulator (similar to a pacemaker) under the collarbone. Everything is under the skin — nothing can be seen from outside. The stimulation can be adjusted at any time, switched off, and — if ever necessary — the system can be removed.
Which brain target?
- Vim (ventral intermediate nucleus of the thalamus) — the classic tremor target.
- PSA (posterior subthalamic area) — just below the Vim, where the cerebellar fibers carrying the tremor signal run in a compact bundle. Studies suggest the PSA may be a more efficient tremor target than the Vim [5].
- Vim + PSA together (double target) — one trajectory reaches both. Each contact is tested and the best one, or a combination, is used. See double-target DBS.
- GPi (globus pallidus internus) — chosen when dystonia, rather than tremor, is the main problem.
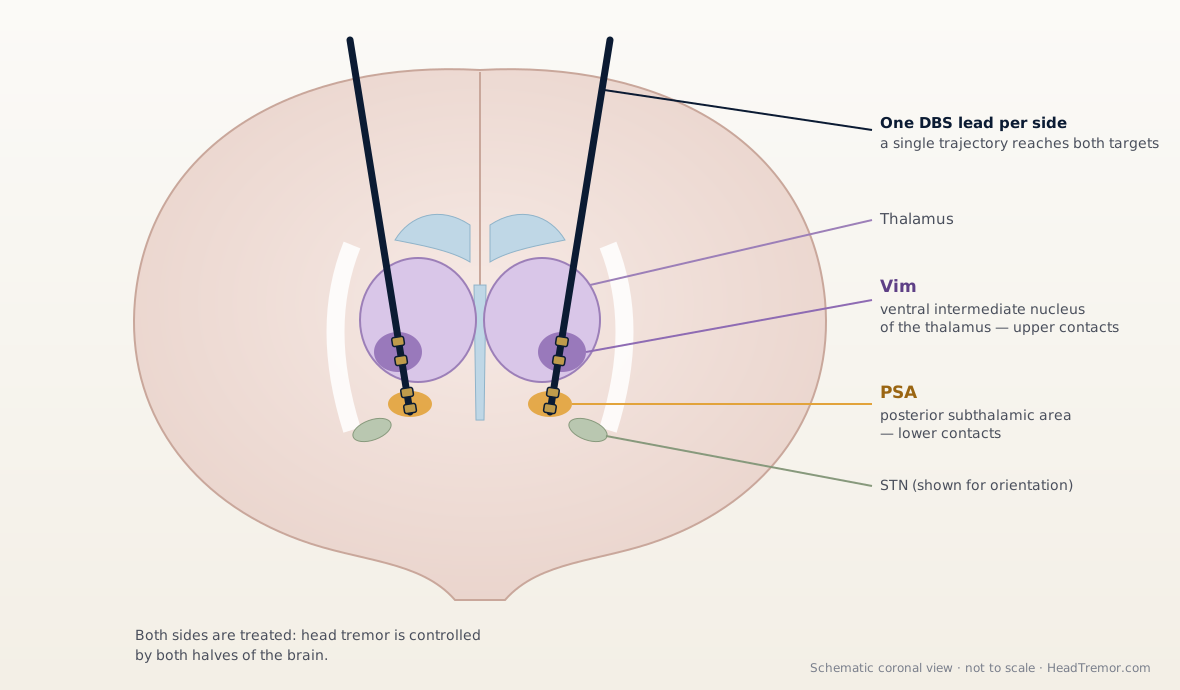
Why both sides of the brain are treated
The neck muscles are controlled by both sides of the brain, and it is very difficult to tell which side drives a head tremor. Studies show greater improvement in head and voice tremor when both sides are stimulated [6],[7], and in a large trial the second side added further improvement in midline tremor [1]. For these reasons, and because tremor conditions tend to progress, we operate on both sides in head tremor. One-sided surgery is considered only for a clearly one-sided dystonic tremor.
The operation, step by step
- Evaluation: a neurologist, psychologist, cardiologist, anesthesiologist, physiotherapist, nutrition specialist and Prof. YILMAZ each assess the patient; the final decision is his.
- Planning: 3 Tesla MRI with contrast under general anesthesia gives a sharp, motion-free image. The trajectory is planned to avoid blood vessels and to keep as many electrode contacts as possible inside the Vim and the PSA.
- Mapping (awake): under local anesthesia, test microelectrodes 2 mm apart are passed on both sides. Their recordings and test stimulation, with the patient awake, show which track gives the best tremor control with the fewest side effects. An interpreter stays with the patient throughout.
- Implantation: the final electrodes are placed and their position is confirmed by CT. The stimulator is implanted under the collarbone under general anesthesia, usually the same day.
- Switch-on the next day: every contact is tested one by one and the stimulator is set on the most effective one. After a successful operation, the tremor stops almost as soon as stimulation begins.
- Follow-up: settings are refined during the stay and then remotely by secure video call. Remote programming by secure video call is free for 3 to 5 years, depending on the package chosen; after that it remains available, without limit, for a fee.
What results look like
Published evidence from our center
Yilmaz A, Eray HA, Cakir M, Ceylan M, Blomstedt P. Deep Brain Stimulation with Double Targeting of the VIM and PSA for the Treatment of Rare Tremor Syndromes. Stereotactic and Functional Neurosurgery 2024;102:224–239.
- 22 patients treated between 2019 and 2023 with bilateral Vim+PSA DBS: 7 isolated head tremor, 4 dystonic tremor, 8 Holmes tremor, 2 voice tremor and 1 tremor caused by liver disease.
- Mean tremor score fell from 3.70 to 0.45 at 12 months; mean tremor reduction 89% (range 50–100%).
- 6 of 7 patients with isolated head tremor reached a tremor score of 0.
- Ratings were made blindly, with stimulation on and off, by two movement disorder specialists.
- To the authors’ knowledge, the largest published case series of double-target Vim+PSA DBS in rare tremor syndromes [5].
Read the article on PubMed (PMID 38934181) · How the double-target technique works
Our longest-followed head tremor patient still has a tremor score of 0 six and a half years after double-target DBS; the score was 4 before surgery (our case series; results vary). Some studies report that the benefit of Vim-only stimulation can fade over years in some tremors [5]. With double targeting, if the effect lessens or the disease progresses, the second target can be added by reprogramming.
Side effects and how they are handled
Stimulation side effects usually appear when the stimulator is first switched on or when settings are increased, and most disappear when the settings are adjusted. In our published series [5]:
- Tingling (paresthesia) was the most common effect when stimulation began; it faded within minutes without any change of settings.
- Slurred speech appeared in one patient after the first electrode, lasted two weeks and resolved by itself; the second side was operated after it had settled.
- Unsteadiness occurred in two patients: in one it resolved by itself, in the other after the active contact was moved slightly upward within the Vim and the PSA share was reduced.
Speech side effects were a known drawback when only the Vim was used. In our experience, the PSA is safer than the Vim with respect to speech, and because both targets sit on the same electrode, we can move stimulation away from a site that causes a problem. A well-placed electrode is the key: if an electrode lies too far to the side, speech effects can persist, which is why placement is checked by testing during surgery and by CT afterward [5].
Surgical complications are uncommon but real. In the published series, one electrode needed repositioning and two patients developed an infection requiring removal of an electrode, which was later re-implanted in one of them [5]. Your individual risk is discussed during the evaluation.
Recovery
- Hospital stay of about 5–6 days; the full program in Istanbul lasts about 10–14 days, or 18 days in the extended package.
- Stitches are removed on day 12; showering is allowed three days later.
- Hair can be dyed and combed normally after one month; swimming, sauna and hammam after one month.
- Wounds are closed cosmetically, so scars are usually barely visible.
Details: recovery after DBS.
Questions to ask before choosing DBS
- What type of tremor do I have, and how sure is the diagnosis?
- Which target will be used, and why?
- Will both sides be operated on?
- Who will perform the operation, and how many tremor operations has the surgeon done?
- When will the stimulator be switched on, and who will program it after I go home?
- What happens if the effect lessens in the future?
Frequently asked questions
Does DBS cure head tremor?
How quickly does DBS work for head tremor?
Am I awake during DBS surgery?
Will my speech or balance be affected?
How long does the battery last?
Can DBS be done if botulinum toxin injections did not help?
Can I be assessed without traveling?
Sources
- Mitchell KT, et al. Benefits and risks of unilateral and bilateral ventral intermediate nucleus deep brain stimulation for axial essential tremor symptoms. Parkinsonism Relat Disord 2019;60:126–132. scholars.duke.edu/publication/1349961
- Anis S, et al. Efficacy of ventral intermediate nucleus deep brain stimulation for head tremors in essential tremor: a single-center retrospective analysis (54 patients). Mov Disord 2025;40(suppl 1) — congress abstract. www.mdsabstracts.org/abstract/efficacy-of-ventral-intermediate-nucleus-deep-brain-stimulation-for-head-tremors-in-essential-tremor-a-single-center-retrospective-analysis/
- Pauls KA, et al. Deep brain stimulation in the ventrolateral thalamus/subthalamic area in dystonia with head tremor. Mov Disord 2014;29(7):953–960. doi.org/10.1002/mds.25884
- Thalamic deep brain stimulation for dystonic head tremor: a long-term study of 18 patients. Mov Disord Clin Pract. onlinelibrary.wiley.com/doi/abs/10.1002/mdc3.70266
- Yilmaz A, Eray HA, Cakir M, Ceylan M, Blomstedt P. Deep Brain Stimulation with Double Targeting of the VIM and PSA for the Treatment of Rare Tremor Syndromes. Stereotact Funct Neurosurg 2024;102:224–239. DOI 10.1159/000539162. pubmed.ncbi.nlm.nih.gov/38934181/
- Putzke JD, Uitti RJ, Obwegeser AA, Wszolek ZK, Wharen RE. Bilateral thalamic deep brain stimulation: midline tremor control. J Neurol Neurosurg Psychiatry 2005;76(5):684–690. pmc.ncbi.nlm.nih.gov/articles/PMC1739619/
- International Essential Tremor Foundation. Deep Brain Stimulation. essentialtremor.org/resource/deep-brain-stimulation/
